Ventilator Care Adult Family Home Placement in Washington
When a loved one requires mechanical ventilation, we help families and discharge planners identify adult family home options in Washington that may be able to evaluate the documented care needs — including 24/7 skilled nursing, equipment, and backup power considerations.

Who This Placement Is For
Ventilator care placement is for ventilator-dependent adults who need a residential setting with around-the-clock skilled nursing, ongoing respiratory monitoring, and emergency readiness — people who would otherwise remain in a hospital or skilled nursing facility. Families navigating this transition often start with our family placement guidance, while hospital teams use our discharge planner support to move complex respiratory discharges forward.
Not every ventilator patient is a candidate for an adult family home. We help you understand which homes may be able to evaluate the documented care needs, and we are transparent when a setting cannot.
Why This Care Need Can Be Difficult to Place
Ventilator support is one of the most challenging care needs to place in a home setting. Only a small number of adult family homes hold Private Duty Nursing (PDN) contracts and carry the equipment and protocols that ventilator care requires, and demand regularly outpaces that limited supply.
- Skilled nursing coverage — 24/7 RN or LPN supervision is typically required, which most homes are not set up to provide.
- Equipment and backup power — Homes must maintain ventilators, oxygen, suction, monitors, and generator or battery backup for outages.
- Emergency readiness — Staff must respond to alarms, disconnection, and respiratory distress while coordinating with EMS.
- Discharge timing — Hospital teams are under pressure to discharge, but ventilator placements are fewer and matching takes care.
Understanding Ventilator Dependence
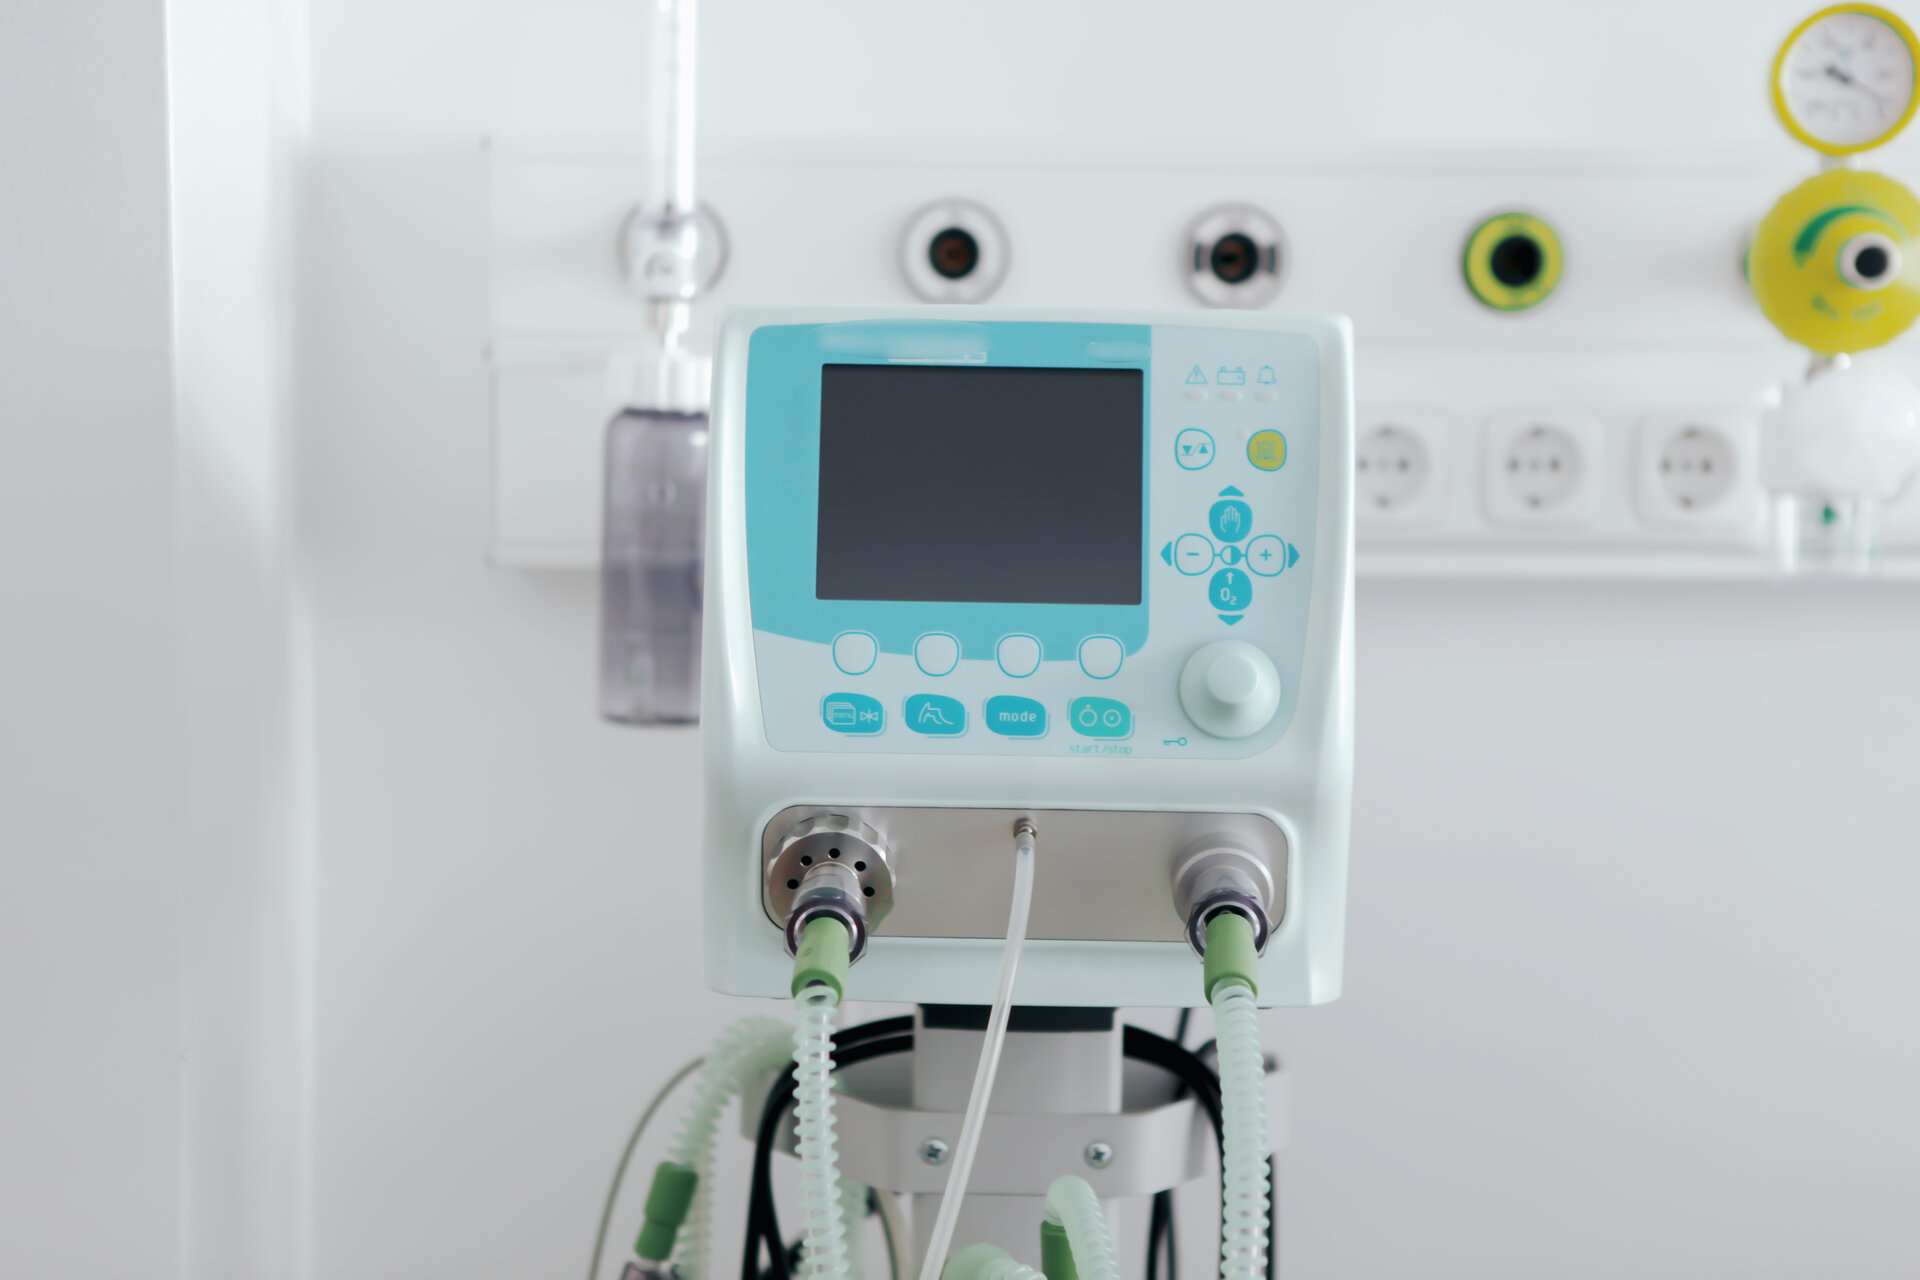
Ventilators (also called mechanical ventilators or respirators) are machines that help people breathe when they cannot breathe adequately on their own. According to the American Thoracic Society, people may need ventilator support due to:
- Neuromuscular diseases: ALS, muscular dystrophy, spinal cord injuries
- Respiratory conditions: COPD, respiratory failure, lung damage
- Post-surgical needs: After certain surgeries or prolonged intubation
- Neurological events: Stroke, brain injury affecting breathing control
- Chronic conditions: Requiring ongoing respiratory support
Types of Ventilation
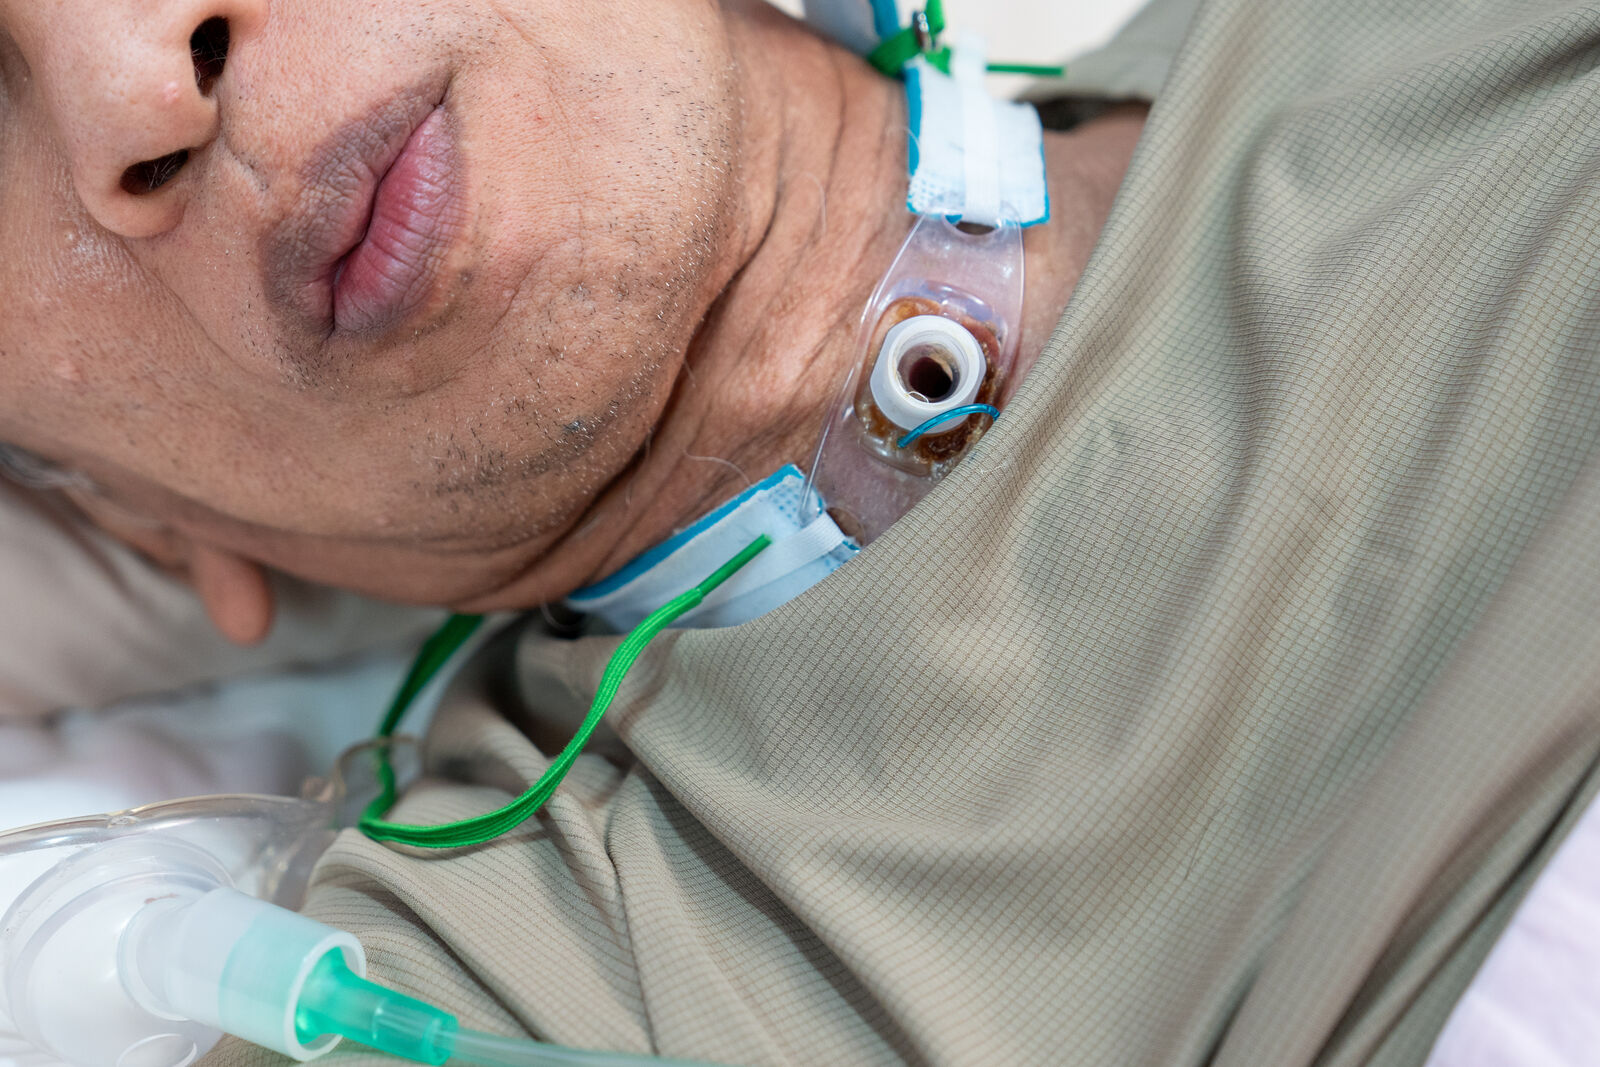
- Invasive ventilation: Delivered through a tracheostomy (an opening in the neck)
- Non-invasive ventilation (NIV): Delivered through a mask (BiPAP, CPAP)
Adult family homes can provide both types of ventilator care, depending on their licensing and staff training. For airway management specifically, see our guide to tracheostomy care and what families need to know.
How Ventilator Care Works in an AFH
A ventilator-dependent patient in an adult family home is not the same as a ventilator patient in an ICU. In an AFH, the model is:
- 24/7 supervision by trained caregivers, overseen by a licensed nurse
- Skilled nursing hours delivered under a private duty nursing (PDN) contract — usually 8–24 hours of nursing per day depending on the patient
- Equipment monitoring — ventilator alarms, suction, and airway care handled by trained staff
- Emergency protocols — backup power, oxygen, and clear escalation to EMS
The AFH brings the home; the PDN team brings the nursing. The two together make home-scale vent care possible and sustainable.
Is It Safe? What the Research Shows
Home and community-based ventilator care is an established, well-studied model. For stable ventilator-dependent patients, outcomes in home settings are comparable to facility care, with quality-of-life advantages and lower cost. Washington's DSHS supports ventilator care in adult family homes for eligible residents through the appropriate rate structure and PDN authorization — this is a recognized placement, not a workaround.
Why Families Choose an AFH for Vent Care
Specialized adult family homes offer several advantages over institutional settings:
- Home-like environment: More comfortable than a hospital or nursing facility
- Personalized attention: Lower resident-to-caregiver ratios
- Consistent caregivers: Staff who know the individual and their equipment
- Family involvement: More accessible visiting and participation
- Quality-of-life focus: Activities and engagement, not just medical care
- Cost-effectiveness: Often less expensive than skilled nursing facilities
What a Vent-Capable Home Must Have
Adult family homes providing ventilator care must have:
- Specialized licensing from Washington DSHS
- Staff with ventilator-specific training and competency verification
- Primary and backup ventilators, oxygen concentrators, suction equipment, pulse oximeters, and emergency supplies including Ambu bags
- Backup power systems — generator or battery — to maintain life-sustaining equipment during outages
- Written emergency protocols, regular drills, and established relationships with local EMS and respiratory therapists
- 24-hour awake staff capable of vent management
- Regular pulmonologist oversight and protocols for ventilator settings and weaning attempts
What to Look For — Questions to Ask and Red Flags
When you tour a potential home, bring these questions:
- How long have you provided ventilator care, and how many vent-dependent residents do you currently have?
- What training do your staff receive for ventilator management, and how often is refresher training done?
- What is your emergency protocol for vent malfunction or respiratory distress?
- Do you have backup power and equipment, and how is it tested?
- Who provides respiratory therapy services, and who manages ventilator settings?
- How do you handle tracheostomy care and suctioning, and what is your staffing ratio for vent patients?
Red flags: vague answers about training or experience, no relationship with respiratory therapists, inadequate backup equipment or power, staff who seem unfamiliar with the ventilator equipment, and no clear emergency protocols.
An RN-operated home brings clinical leadership on site by design, which is a meaningful advantage for vent residents. For a real-world example, read our case study of a vent patient placed in 48 hours.
Cost and Funding
Ventilator care is among the highest-cost services in adult family homes. Typical costs in the Seattle area:
| Care Level | Monthly Cost Range |
|---|---|
| Non-invasive ventilation (BiPAP/CPAP) | $10,000 - $14,000 |
| Invasive ventilation (tracheostomy) | $14,000 - $22,000+ |
Funding typically comes from one of these places:
- Medicaid (DSHS/COPES) — the most common route; the patient's assessment determines the rate, and PDN hours are authorized separately. The DSHS COPES program provides enhanced payment rates for ventilator care, making this option accessible for Medicaid-eligible individuals.
- Medicare — limited to short-term skilled needs in qualifying circumstances
- Private pay — families paying directly, sometimes combining funding sources
- Veterans benefits — may supplement care costs
- Long-term care insurance — check your policy for high-acuity coverage
Our Medicaid rate estimator can help you understand what a vent patient's care may be funded at before you start the search.
Day-to-Day Ventilator Care
Typical care activities for a ventilator resident include:
- Continuous ventilator monitoring
- Tracheostomy care and cleaning
- Suctioning as needed
- Equipment maintenance and troubleshooting
- Respiratory assessments
- Medication administration
- Communication support (many vent patients have limited speech)
Good ventilator care goes beyond medical management — communication aids, positioning for comfort and activities, social engagement, mobility support, and family involvement all matter for quality of life.
Transitioning to an Adult Family Home
From the Hospital
Discharge from a hospital to an AFH requires coordination:
- Equipment setup at the new location
- Training of AFH staff on the individual's specific needs
- Transfer of medical records and care plans
- Arrangement of respiratory therapy services
- Follow-up appointments scheduled
Discharge planners coordinating a ventilator transition can find practical guidance in our resources for discharge planners.
From Another Facility
Transferring from a nursing home or other setting involves assessment by the receiving AFH, equipment compatibility verification, medication and care plan transfer, and trial-period arrangements.
What Information SALN Needs to Begin Matching
To begin matching, we ask families and referral professionals to share the documented care picture, including:
- Ventilator settings, mode, and weaning history or potential
- Tracheostomy type and suctioning frequency, if present
- Required nursing hours and whether PDN is in place or being pursued
- Co-occurring diagnoses, medications, and equipment list
- Current location, discharge timeline, and payer or funding status
Complete clinical information lets us have realistic conversations with homes and avoid dead-end referrals. Discharge planners can share this with us directly through our planner intake process.
Placement Factors We Discuss and Verify
Before presenting potential options, we discuss current availability, provider acceptance criteria, staffing, equipment, payer considerations, location, and care-coordination needs. Final acceptance and clinical care planning remain with the provider and clinical team.
Respiratory Equipment
Primary and backup ventilators, oxygen concentrators, suction equipment, pulse oximeters, and emergency supplies including Ambu bags.
Private Duty Nursing
PDN contracts providing RN or LPN coverage trained in ventilator management and respiratory emergencies.
Backup Power
Generator systems and battery backup to maintain life-sustaining equipment during power outages.
Emergency Protocols
Written emergency procedures, regular drills, and established relationships with local EMS and respiratory therapists.
Physician Oversight
Regular pulmonologist visits and protocols for ventilator settings, weaning attempts, and respiratory management.
Hospital Access
Proximity to hospitals with respiratory ICU capabilities for emergency situations.
Questions Families and Discharge Planners Should Ask
These questions help both families and referral professionals evaluate whether a potential home is a realistic match for ventilator care:
- What nursing coverage is available around the clock, and who manages ventilator settings?
- What happens during a power outage, and how is backup power tested?
- How are suctioning, weaning, and respiratory emergencies handled, and who is on call?
- Is the home willing to accept the documented care needs, and what does it require before admission?
- What payer arrangements does the home accept for ventilator care?
Families can bring these questions to tours, and discharge planners can ask them during provider calls — we help coordinate both conversations through our placement process.
Washington Service Coverage and Constraints
SALN helps identify adult family home and assisted living options across Washington State, with the deepest network of high-acuity homes in the greater Seattle area, King County, and Snohomish County. For families prioritizing the Seattle metro region, our King County placement page outlines the local landscape.
Local ventilator care placement coverage is available in Seattle, Bellevue, Kirkland, Tacoma, Everett, and Redmond.
Constraints matter for ventilator care: availability is limited to homes with active PDN arrangements, and timelines depend on funding decisions, equipment transfer, and provider acceptance. We are upfront about these constraints rather than promising a fast or certain outcome. You can review how matching and coordination work to understand what happens next.
Related Services
Related Resources
Frequently Asked Questions
Can adult family homes really provide ventilator care?
Washington State allows adult family homes to care for ventilator-dependent residents when they have appropriate Private Duty Nursing contracts and meet specific licensing requirements. Many families prefer the home-like setting over an institutional ventilator unit, but suitability depends on the individual care picture and the small number of homes able to support it.
What is Private Duty Nursing and why is it required?
Private Duty Nursing provides dedicated skilled nursing care, typically an RN or LPN, for a specific patient. For ventilator residents, PDN nurses manage the ventilator, monitor respiratory status, and handle emergencies in addition to standard caregiving.
Does Medicaid cover ventilator care in adult family homes?
Washington Medicaid can cover both the AFH room and board (through COPES) and Private Duty Nursing hours for eligible residents. Coverage depends on medical necessity and eligibility, and acceptance remains with the provider and payer.
What happens if there's a power outage?
Qualified ventilator care homes must have backup power systems — typically battery backup on the ventilator itself plus a generator or alternative power source for the home. They should also have manual resuscitation bags available. Ask about their backup power protocols and how long they can operate without main power.
How do I know if staff are properly trained for ventilator care?
Ask to see documentation of ventilator-specific training and competency verification. Staff should be trained by respiratory therapists or other qualified professionals, and should be able to demonstrate equipment operation, troubleshooting, emergency procedures, and tracheostomy care. Ask how often refresher training occurs.
How do you verify a home can safely support a ventilator resident?
We discuss backup power, emergency protocols, equipment maintenance, nursing qualifications, and hospital proximity before presenting a potential option. The final appropriateness decision rests with the provider and clinical team.
What if my family member is weaning from the ventilator?
Some adult family homes can support weaning protocols under physician guidance. We identify homes with relevant experience and coordinate with the pulmonology team as part of the care plan.
How quickly can you help with a ventilator placement?
Ventilator placements require careful matching and are more limited than standard placements. We typically aim to present potential options within a few days when complete information is provided, though hospital discharge coordination may extend timelines.
Need Ventilator Care Placement Help?
We help families and discharge planners identify adult family home options that may be able to evaluate the documented care needs. There is no cost to families, and referrals are handled confidentially.